
MSR Runner’s Maintenance, Part 2: Core
Updated: 7 hours ago

A runner may begin a session feeling capable, then develop back discomfort or increasing trunk fatigue as the distance builds. For someone preparing for an event or protecting a valued running routine, the question is practical: what needs attention so training remains sustainable?
This instalment examines abdominal and spinal muscle contributions to running, connecting assessment with MSR manual care and physical preparation. Practitioners will consider relevant movement, loading, and endurance findings, then determine which deserve treatment. The purpose is to support the runner’s ability to manage changing demands, with useful improvements carried into exercise, repeated strides, and continued participation.
Here, core refers principally to the trunk musculature, with particular attention to transversus abdominis, rectus abdominis, the internal and external obliques, and erector spinae. Multifidus, quadratus lumborum, the diaphragm, and other structures also contribute according to the task.
These muscles help coordinate spinal, rib-cage, and pelvic movement while responding to repeated loading. Running requires adaptable control rather than a rigid torso or continuous maximal bracing. Their relevance is assessed through symptoms, movement, and physical capacity.
Article Index

Abdominal Muscles: Movement and Loading Capacity
Anatomical involvement: Rectus abdominis contributes to trunk flexion; the obliques contribute to rotation, lateral flexion, and trunk control. Transversus abdominis contributes to abdominal-wall tension and pressure regulation. Their activity changes with the task.
Clinical interpretation: Trunk symptoms, painful rotation, or difficulty sustaining running may justify examination of abdominal loading capacity and relevant spinal or hip movement. Trunk lean, pelvic position, or visible abdominal shape cannot establish weakness or instability.
MSR treatment priorities: Consider relevant rectus abdominis, oblique, or associated regional findings when examination supports treatment. Adapt positioning, contact, movement, and breathing coordination to the demonstrated procedure and patient response. Reassess a meaningful movement or loading task.
Examination Findings That May Influence Care
Palpation can identify tenderness, reproduce familiar symptoms, and help assess tolerance to contact. Record the location and response alongside movement and resisted loading. A firm or sensitive area does not independently confirm an adhesion, fibrosis, or a muscle injury.
Assess relevant trunk flexion, rotation, and endurance using tasks suited to the presentation. Compare these findings with the runner’s symptoms and training demands. Abdominal appearance is not a measure of activation, and anterior pelvic tilt alone does not establish shortening.
Precautions: Explain abdominal contact and obtain consent. New or unexplained abdominal pain, a suspected hernia, or systemic symptoms require appropriate assessment before local treatment.
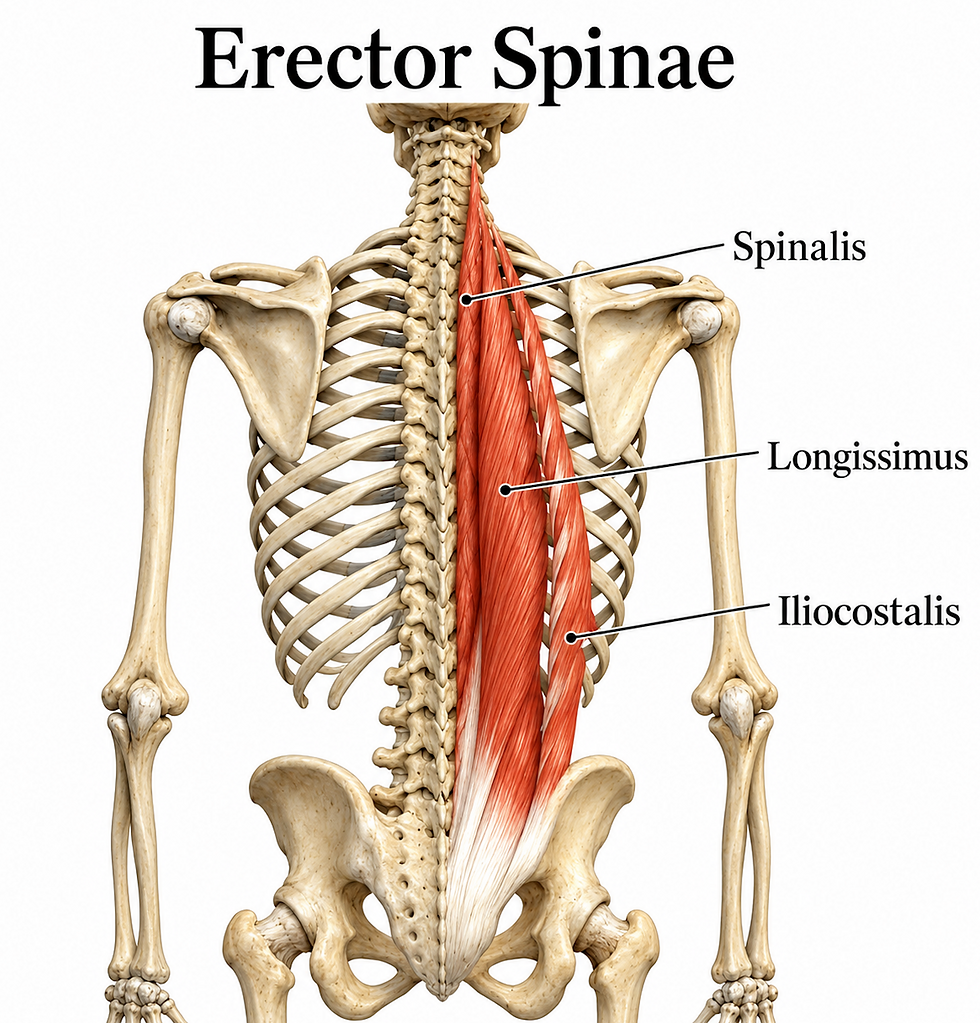
Erector Spinae: Spinal Movement and Endurance
Anatomical involvement: The erector spinae group comprises iliocostalis, longissimus, and spinalis. These muscles contribute to spinal extension, lateral flexion, and control during movement and loading, coordinating with other trunk and hip muscles.
Clinical interpretation: Back pain during running, painful spinal movement, or limited endurance may justify focused assessment. Forward lean can be a running strategy and does not establish spinal-extensor weakness.
MSR treatment priorities: Consider relevant thoracic or lumbar erector spinae, multifidus, quadratus lumborum, and joint findings when they influence the runner’s limitation. Connect treatment with active movement and progressive trunk or hip loading, then reassess the affected task.
Reason: Trunk posture can redistribute lower-limb demands. It should not automatically be framed as mechanical failure or inefficiency. pubmed.ncbi.nlm.nih.gov
Examination Findings That May Influence Care
Assess tenderness, familiar symptom reproduction, spinal movement, and tolerance to repeated or sustained loading. Palpation helps guide contact and treatment response; texture alone cannot establish underlying fibrosis or explain the running limitation.
Observe whether trunk lean, rotation, or lateral movement changes with symptoms or fatigue. Compare with relevant strength, endurance, and mobility findings rather than treating asymmetry as a diagnosis.
Progressive neurological changes or other concerning findings require further assessment. Persistent focal back pain in a young runner also warrants consideration of a bone stress injury.

Core: Observation and Clinical Interpretation
Observe several strides from the side, front, and behind at comparable speeds. Record symptoms and changes as running continues.
Trunk position: Does lean change with symptoms or fatigue? Examine relevant movement and capacity before recommending a change.
Rotation: Is rotation painful or difficult to sustain? Consider thoracic movement, arm swing, and pelvic coordination.
Lateral control: Do side-to-side changes coincide with symptoms or declining tolerance? Compare with appropriate trunk and single-leg tasks.
Breathing and effort: Does the runner report breath-holding or excessive bracing? Explore whether the strategy serves the task.
Repeated performance: Does the concern emerge with duration, pace, or hills? Assess at an appropriate demand and review training and recovery.
Use observations to form a clinical question, then test it.
Motion Specific Release (MSR): Runner’s Maintenance
Select abdominal, spinal, or joint procedures according to findings that influence symptoms or function. Establish a baseline, adapt the application to the patient, and reassess whether treatment produces a useful change.
Build on that response with exercises selected for the runner’s needs. Options may include modified side planks, bird dogs, resisted trunk rotation, or carries. Adjust position, resistance, duration, repetitions, and breathing rather than prescribing the same routine to everyone.
Progress toward the endurance and movement demands of running. An improved exercise score is useful, but also check whether symptoms and participation improve across training sessions.
These recommendations combine anatomical reasoning and clinical application. Research on core exercise does not directly establish MSR treatment effects or show that every runner requires trunk treatment.
Evidence note: A small running trial reported improved 5,000-m performance after core training, without significant changes in its measured ground-reaction-force or lower-limb stability outcomes. This supports separating performance findings from proposed mechanisms.

Core MSR Demonstration Video
Dr. Abelson demonstrates MSR procedures for the trunk region. Select components according to the examination, adapt application to patient feedback, and reassess the movement or loading task that prompted treatment.
Conclusion
Trunk assessment becomes useful when it helps explain a runner’s symptoms or difficulty sustaining the intended workload. Abdominal and spinal findings can guide specific MSR procedures, while exercise develops the strength, endurance, and coordination required across repeated strides.
Maintenance should support the runner’s ability to participate and manage changing demands. Reassess whether improvements carry into training, adjust preparation as capacity develops, and reconsider the plan when progress stalls. The objective is to help preserve a meaningful part of the person’s life. Part 3 examines the hips and their contributions to movement and loading.
References
Novacheck TF. The biomechanics of running. Gait & Posture. 1998;7(1):77–95.
Sato K, Mokha M. Does core strength training influence running kinetics, lower-extremity stability, and 5000-M performance in runners? Journal of Strength and Conditioning Research. 2009;23(1):133–140.
Teng HL, Powers CM. Influence of trunk posture on lower extremity energetics during running. Medicine & Science in Sports & Exercise. 2015;47(3):625–630.
DR. BRIAN ABELSON DC. - The Author

Dr. Brian Abelson is a chiropractor, author, and educator with more than 30 years of clinical experience in musculoskeletal care, rehabilitation, and sports performance. His educational work focuses on musculoskeletal conditions, human movement, sports biomechanics, and evidence-informed approaches to treatment and rehabilitation.
He is the developer of Motion Specific Release (MSR) and Clinical Director of Kinetic Health in Calgary, Alberta, Canada.

Continue Learning with MSR Courses and MSR Pro
For Healthcare Practitioners
Motion Specific Release integrates assessment, clinical reasoning, manual therapy, exercise, and patient education within one adaptable approach to musculoskeletal care.
MSR Pro and MSR courses support different parts of that learning process:
Structured Clinical Education: MSR courses connect applied anatomy and biomechanics with orthopedic and neurological assessment, myofascial procedures, fascial expansions, joint mobilization, manipulation, and rehabilitation.
Hands-On Skill Development: Live training provides opportunities to refine palpation, patient positioning, force application, and clinical decision-making through practice and direct feedback.
MSR Pro Clinical Library: Members receive access to more than 200 MSR procedures, downloadable and fillable clinical forms, examination resources, rehabilitation progressions, and exercise-prescription materials.
Extensive Video Resources: More than 800 videos support examination, treatment procedures, exercise rehabilitation, and clinical application.
Patient Education: A library of 50 condition articles helps practitioners explain common musculoskeletal problems and provide patients with practical information.
Continued Development: Resources are updated as MSR courses and clinical education continue to evolve.
Videos and articles can introduce concepts, but hands-on proficiency develops through deliberate practice, feedback, and experience. MSR is designed to help practitioners connect technique with clinical reasoning and adapt care to the individual rather than apply the same protocol to everyone.
Explore MSR Pro | View Online and Live Courses
Disclaimer:
The content on the MSR website, including articles and embedded videos, serves educational and informational purposes only. It is not a substitute for professional medical advice; only certified MSR practitioners should practice these techniques. By accessing this content, you assume full responsibility for your use of the information, acknowledging that the authors and contributors are not liable for any damages or claims that may arise.
This website does not establish a physician-patient relationship. If you have a medical concern, consult an appropriately licensed healthcare provider. Users under the age of 18 are not permitted to use the site. The MSR website may also feature links to third-party sites; however, we bear no responsibility for the content or practices of these external websites.
By using the MSR website, you agree to indemnify and hold the authors and contributors harmless from any claims, including legal fees, arising from your use of the site or violating these terms. This disclaimer constitutes part of the understanding between you and the website's authors regarding the use of the MSR website. For more information, read the full disclaimer and policies in this website.



Comments