
Meniscus Injuries Part 1: Understanding Meniscus Injuries
Updated: Oct 7

A Closer Look at the Knee's Resilient Crescent
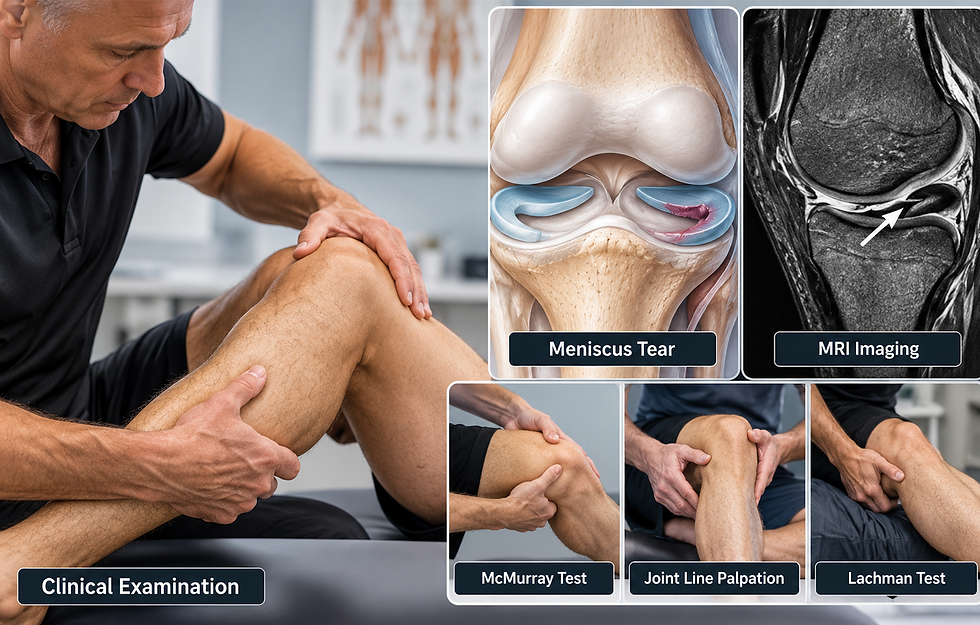
The menisci are two crescent-shaped structures within the knee that play an important role in load distribution, joint stability, shock absorption, and movement. Their name comes from the Greek word for “crescent,” reflecting their characteristic shape.
Meniscus injuries are common, but finding a meniscal tear does not automatically mean that surgery is required. Management depends on several factors, including whether the tear is traumatic or degenerative, its location and pattern, associated injuries, the patient's symptoms and functional limitations, and the demands they place on the knee.
Many patients can be successfully managed without surgery through education, appropriate activity modification, and progressive exercise rehabilitation. Some injuries, however, warrant earlier orthopaedic evaluation, particularly displaced tears that restrict knee motion, potentially repairable acute traumatic tears, and other tear patterns in which delaying intervention could compromise meniscal function or treatment options.
Article Index:
What Causes Meniscal Injuries
Meniscal injuries can occur through different mechanisms, but clinically they are often divided into two broad categories: acute traumatic tears and degenerative meniscal lesions.
Traumatic Meniscal Tears
Traumatic tears are commonly associated with sports such as football, basketball, soccer, rugby, skiing, and other activities involving rapid changes in direction, pivoting, or contact.
A typical mechanism involves rotation of the femur and tibia while the knee is flexed and the foot is relatively fixed. The combination of compression, rotation, and shear can place substantial stress on the meniscus.
Traumatic tears can take several forms, including vertical longitudinal, radial, flap, bucket-handle, and root tears. The tear pattern is clinically important because it influences meniscal function, mechanical stability, healing potential, and decisions regarding conservative management or surgical repair.
Meniscal injuries may also occur in combination with ligament injuries. A well-known example is the combination of injuries involving the ACL, MCL, and medial meniscus, historically referred to as the unhappy triad. However, meniscal injury patterns associated with ACL trauma vary, and the lateral meniscus is also commonly injured during acute ACL injury.
Degenerative Meniscal Lesions
Meniscal tissue changes across the lifespan. Age-related alterations in collagen organization, cellular activity, tissue composition, and mechanical properties can influence how the meniscus responds to loading and injury.
Degenerative meniscal lesions typically develop without a single major traumatic event. Symptoms may begin gradually or appear during an ordinary activity such as squatting, kneeling, twisting, or rising from a low position.
These lesions become increasingly common from middle age onward and frequently coexist with other age-related changes within the knee. Importantly, a degenerative meniscal tear identified on MRI does not necessarily mean that the tear is responsible for the patient's symptoms.
This distinction has important treatment implications. Exercise-based nonoperative management is generally the first-line approach for degenerative meniscal lesions, while selected acute traumatic tears may require earlier orthopaedic evaluation, particularly when meniscal repair may be possible.
Meniscus Injuries and Osteoarthritis
The menisci play an important role in distributing load across the knee, absorbing forces, contributing to joint stability, and protecting the articular cartilage. Loss of normal meniscal function can increase contact stresses within the knee and is associated with the development and progression of osteoarthritis.
This relationship is particularly important when surgery is being considered. When surgical treatment is indicated, contemporary management emphasizes preserving as much functional meniscal tissue as possible. Repair is preferred over partial meniscectomy when the tear pattern, tissue quality, vascularity, and clinical circumstances make successful repair reasonably possible.
At the same time, degenerative meniscal lesions and knee osteoarthritis frequently occur together. In these cases, the meniscal finding should be interpreted within the broader clinical picture rather than automatically considered the primary source of pain.
Anatomy & Biomechanics of Meniscus Injuries

The medial and lateral menisci are crescent-shaped fibrocartilaginous structures positioned between the femoral condyles and tibial plateau.
Far from being simple cushions, they are highly organized structures that contribute to load distribution, shock absorption, joint congruity, stability, lubrication, and proprioceptive function.
Each meniscus has a wedge-shaped cross-section, thicker around its peripheral border and thinner toward its free inner edge. This shape helps increase the contact area between the relatively rounded femoral condyles and the tibial plateau, distributing forces across a larger surface and reducing peak stresses on the articular cartilage.
The medial and lateral menisci are not biomechanically identical. The medial meniscus is more firmly attached to the surrounding capsule and associated structures and is therefore less mobile. The lateral meniscus is more mobile and can undergo greater displacement as the knee moves through flexion, extension, and rotation. These anatomical differences influence both meniscal function and patterns of injury.
From Compression to Hoop Stress
One of the most important biomechanical functions of the meniscus is its ability to convert compressive forces into circumferential tensile forces, commonly called hoop stresses.
When the femur compresses the meniscus against the tibial plateau, the wedge-shaped meniscus tends to be displaced outward. Its circumferential collagen fibres, together with its root and peripheral attachments, resist this displacement and distribute the load around the meniscus.
This organization allows the meniscus to transmit substantial loads while protecting the underlying articular cartilage.
This concept becomes particularly important when considering radial tears and meniscal root tears. Tears that disrupt the circumferential fibre network or detach the meniscus from its root can interfere with hoop-stress transmission, reducing the meniscus's ability to distribute load effectively.
That gives us an important biomechanical principle for the rest of this series:
The clinical significance of a meniscal tear depends not only on its size, but also on its location, orientation, stability, and effect on meniscal function.

Meniscus Motion
The menisci are dynamic structures that move and deform as the knee moves.
During knee flexion, both menisci generally translate posteriorly as they adapt to the changing position of the femoral condyles. During extension, they move anteriorly. Rotation of the tibia and femur also influences meniscal position and loading.
The lateral meniscus is considerably more mobile than the medial meniscus, particularly during knee flexion. This mobility helps it maintain contact with the changing surfaces of the lateral femoral condyle and tibial plateau throughout movement.
The menisci therefore do not simply sit between the femur and tibia. They continuously move, deform, distribute load, and adapt to changing joint positions during walking, running, squatting, jumping, and other activities.
Meniscus Injury and Healing Potential
The ability of a meniscal injury to heal depends on more than the size of the tear. Location, tear pattern, tissue quality, stability, vascular supply, associated injuries, and the patient's age and activity demands can all influence healing and treatment decisions.
Blood Supply and the Meniscal Zones
The meniscus does not have a uniform blood supply. Its outer peripheral region receives vascular supply from branches surrounding the knee, while vascularity progressively decreases toward the inner free edge.
Clinically, the meniscus is often described in vascular zones:
Red-red zone: the vascularized peripheral portion of the meniscus, with the greatest healing potential.
Red-white zone: the transitional region, where vascular supply is reduced.
White-white zone: the inner portion of the meniscus, which has little or no direct vascular supply and therefore has less biological healing potential.
These zones are useful clinically, but they should not be interpreted as absolute boundaries between tears that can and cannot heal. Vascularity is only one factor influencing meniscal healing.
Tear orientation is also important. A longitudinal tear near the vascular periphery may preserve much of the circumferential collagen architecture and may have greater potential for biological healing or surgical repair. In contrast, radial and root tears can disrupt the circumferential fibre network and impair hoop-stress transmission, potentially producing a much greater effect on meniscal load distribution than their size alone might suggest.
Symptoms of a Meniscal Injury
Meniscal symptoms vary considerably depending on whether the injury is traumatic or degenerative, the location and configuration of the tear, associated injuries, and the demands placed on the knee.
Common findings may include:
Pain along the medial or lateral joint line
Swelling or recurrent joint effusion
Pain with loaded knee flexion
Symptoms during squatting, kneeling, twisting, or pivoting
Clicking, catching, or other mechanical sensations
Reduced knee motion
Difficulty with running, stairs, sport, or other weight-bearing activities
Some meniscal tears produce surprisingly few symptoms, particularly degenerative lesions identified incidentally on imaging. Conversely, substantial knee pain does not necessarily indicate a large or unstable tear. Degenerative meniscal abnormalities are common with aging and are not always the source of a patient's symptoms.
Clicking, Catching and True Knee Locking
Clicking or catching does not necessarily mean that a meniscal fragment is mechanically blocking the joint. These symptoms can occur with several knee conditions and should be interpreted alongside the history and physical examination.
True mechanical locking is different. In this situation, the patient is physically unable to fully extend or flex the knee because something is obstructing normal joint motion. A displaced bucket-handle tear is one potential cause.
A genuinely locked knee, particularly following an acute injury, warrants prompt medical or orthopaedic assessment. A displaced or displacing meniscal tear or another intra-articular lesion may be restricting knee motion and may require timely intervention. Contemporary guidelines similarly distinguish potentially repairable or displaced acute tears from the much broader group of meniscal lesions that can initially be managed nonoperatively.
Clinical Perspective
The severity of a meniscal injury should not be judged by pain alone.
A more useful clinical assessment considers the mechanism of injury, tear pattern and location when known, swelling, range of motion, mechanical symptoms, knee stability, associated injuries, functional limitations, and the patient's activity demands.
Understanding the Injury Is the First Step
Meniscal injuries are not all the same. A traumatic longitudinal tear in a young athlete, a displaced bucket-handle tear, a radial or root tear that disrupts hoop tension, and a degenerative meniscal lesion in an older adult can have very different clinical implications.
Understanding these differences begins with the anatomy and biomechanics of the meniscus. Tear location, orientation, vascularity, stability, tissue quality, associated injuries, and the effect of the tear on normal meniscal function all influence healing potential and treatment decisions.
Just as importantly, the presence of a meniscal tear does not automatically identify the source of a patient's knee pain or determine the need for surgery. Symptoms must be interpreted within the broader clinical picture, particularly when degenerative meniscal changes are present.
For many patients, conservative management and progressive rehabilitation can restore function without surgery. Other injuries, particularly displaced tears causing true mechanical locking or certain potentially repairable traumatic tears, may require earlier orthopaedic assessment.
The next step is therefore determining what type of meniscal problem we are dealing with and how clinically significant it is.
In Part 2: Diagnosis and Early Management, we will examine the history, physical examination, orthopaedic testing, imaging, differential diagnosis, and early management strategies used to evaluate meniscal injuries and determine the most appropriate course of care.
References
Abelson B, Abelson K, Mylonas E. A Practitioner's Guide to Motion Specific Release: Utilizing Fascial Expansions, Acupuncture and Manual Therapy. 1st ed. Rowan Tree Books; 2018.
American Academy of Orthopaedic Surgeons. Management of Acute Isolated Meniscal Pathology: Evidence-Based Clinical Practice Guideline. Rosemont, IL: American Academy of Orthopaedic Surgeons; 2024. Published June 10, 2024. AAOS
Arnoczky SP, Warren RF. Microvasculature of the human meniscus. Am J Sports Med. 1982;10(2):90-95. doi:10.1177/036354658201000205.
Beaufils P, Becker R, Kopf S, Englund M, Verdonk R, Ollivier M, Seil R. Surgical management of degenerative meniscus lesions: the 2016 ESSKA meniscus consensus. Knee Surg Sports Traumatol Arthrosc. 2017;25(2):335-346. doi:10.1007/s00167-016-4407-4.
Englund M, Guermazi A, Gale D, et al. Incidental meniscal findings on knee MRI in middle-aged and elderly persons. N Engl J Med. 2008;359(11):1108-1115. doi:10.1056/NEJMoa0800777.
Ina J, Nelson G, Strony JT, et al. Biomechanics of meniscus tears and repair techniques. Curr Rev Musculoskelet Med. 2025;18(9):311-322. doi:10.1007/s12178-025-09963-y.
Kopf S, Beaufils P, Hirschmann MT, et al. Management of traumatic meniscus tears: the 2019 ESSKA meniscus consensus. Knee Surg Sports Traumatol Arthrosc. 2020;28(4):1177-1194. doi:10.1007/s00167-020-05847-3.
Mameri ES, Dasari SP, Fortier LM, Gómez Verdejo F, Gursoy S, Yanke AB, Chahla J. Review of meniscus anatomy and biomechanics. Curr Rev Musculoskelet Med. 2022;15(5):323-335. doi:10.1007/s12178-022-09768-1.
Prill R, Ma CB, Wong SE, et al. The formal EU-US Meniscus Rehabilitation 2024 Consensus: an ESSKA-AOSSM-AASPT initiative. Part II: prevention, non-operative treatment and return to sport. Knee Surg Sports Traumatol Arthrosc. 2025;33(8):3014-3024. doi:10.1002/ksa.12689. ESSKA Journals
Pujol N, Giordano AO, Wong SE, et al. The formal EU-US Meniscus Rehabilitation 2024 Consensus: an ESSKA-AOSSM-AASPT initiative. Part I: rehabilitation management after meniscus surgery. Knee Surg Sports Traumatol Arthrosc. 2025;33(8):3002-3013. doi:10.1002/ksa.12674.
Disclaimer:
The articles and embedded videos on the MSR website are provided for educational and informational purposes only. They are not a substitute for individualized assessment, diagnosis, or treatment by an appropriately qualified healthcare professional.
Some videos demonstrate clinical examination and manual therapy procedures intended for licensed or regulated healthcare professionals with appropriate training. These procedures should be performed only within the practitioner’s legal scope of practice and should not be attempted as self-treatment.
Viewing or using this content does not establish a practitioner-patient relationship. If you have questions about a medical condition or symptoms that are new, severe, or worsening, consult an appropriately qualified healthcare provider.
MSR is not responsible for decisions made or actions taken solely on the basis of this educational content. For complete information about website use, third-party links, privacy, and legal terms, please review the MSR Terms of Use, Privacy Policy, and full website disclaimer.
DR. BRIAN ABELSON, DC. - The Author

Dr. Brian Abelson is a chiropractor, author, and educator with more than 30 years of clinical experience in musculoskeletal care, rehabilitation, and sports performance. His educational work focuses on musculoskeletal conditions, human movement, sports biomechanics, and evidence-informed approaches to treatment and rehabilitation.
He is the developer of Motion Specific Release (MSR) and Clinical Director of Kinetic Health in Calgary, Alberta, Canada.

Continue Learning with MSR Courses and MSR Pro
For Healthcare Practitioners
Motion Specific Release integrates assessment, clinical reasoning, manual therapy, exercise, and patient education within one adaptable approach to musculoskeletal care.
MSR Pro and MSR courses support different parts of that learning process:
Structured Clinical Education: MSR courses connect applied anatomy and biomechanics with orthopedic and neurological assessment, myofascial procedures, fascial expansions, joint mobilization, manipulation, and rehabilitation.
Hands-On Skill Development: Live training provides opportunities to refine palpation, patient positioning, force application, and clinical decision-making through practice and direct feedback.
MSR Pro Clinical Library: Members receive access to more than 200 MSR procedures, downloadable and fillable clinical forms, examination resources, rehabilitation progressions, and exercise-prescription materials.
Extensive Video Resources: More than 800 videos support examination, treatment procedures, exercise rehabilitation, and clinical application.
Patient Education: A library of 50 condition articles helps practitioners explain common musculoskeletal problems and provide patients with practical information.
Continued Development: Resources are updated as MSR courses and clinical education continue to evolve.
Videos and articles can introduce concepts, but hands-on proficiency develops through deliberate practice, feedback, and experience. MSR is designed to help practitioners connect technique with clinical reasoning and adapt care to the individual rather than apply the same protocol to everyone.
Explore MSR Pro | View Online and Live Courses


Comments