
Whiplash Injuries, Part 1: Understanding What Happens During a Collision

Understanding Whiplash-Associated Disorders
Whiplash-associated disorders (WAD) can develop following a motor vehicle collision or other sudden acceleration-deceleration injury. While neck pain and stiffness are common, symptoms can vary considerably and may include headaches, dizziness, neurological symptoms, reduced movement, and difficulty returning to normal activities.
This three-part series explores whiplash from injury through recovery. Part 1 examines what happens to the cervical spine and surrounding tissues during a collision. Part 2 looks at symptoms, examination, diagnosis, and WAD classification. Part 3 focuses on treatment, exercise, and progressive rehabilitation.
Understanding what happens during a whiplash injury provides an important foundation for understanding the symptoms that may follow and how recovery can be approached.
Article Index:
The Rapid Dynamics of Whiplash Injury
To understand whiplash-associated disorders, it helps to first understand what happens during a rear-end collision. The movement is extremely rapid, occurring within a fraction of a second and often before the occupant can consciously react to what is happening.
Whiplash is sometimes described simply as the head moving backward into extension and then forward into flexion. In reality, the biomechanics are more complex. Different regions of the cervical spine move at different times, temporarily creating patterns of motion that do not occur during normal voluntary neck movement.
For simplicity, we can divide the sequence into three stages: the initial impact, extension, and flexion. Understanding these stages helps explain how different cervical structures may be exposed to unusually rapid forces during a collision.
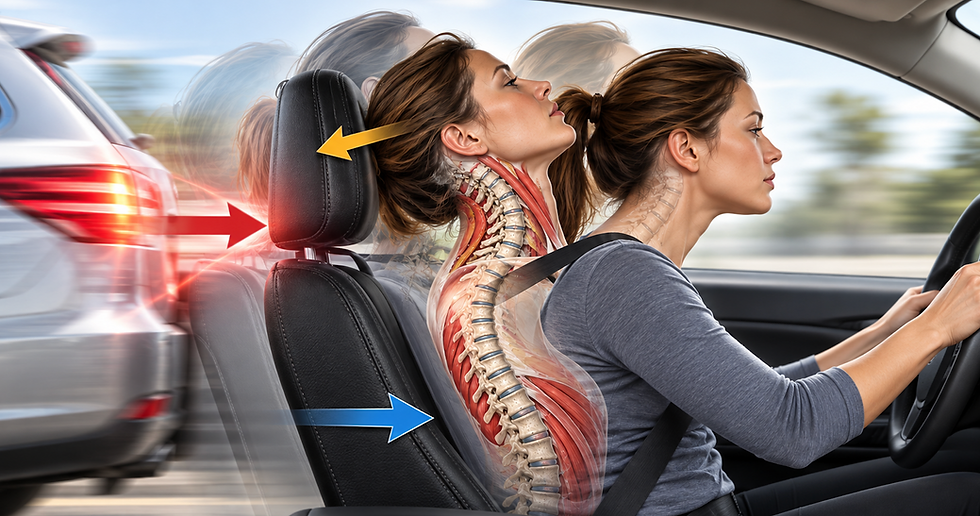
Stage 1: The Initial Impact
Consider a typical rear-end collision. When the vehicle is struck from behind, the vehicle and seat begin moving forward. The seat then transfers force to the occupant's torso, while the head initially lags behind because of inertia.
During these first moments, the torso begins moving forward with the seat while the head has not yet accelerated to the same degree. This creates a complex pattern of movement through the cervical spine.
Rather than the entire neck simply extending backward as one unit, the lower cervical segments can begin extending while the upper cervical region follows a different pattern of motion. For a brief period, this can produce the characteristic S-shaped configuration described in whiplash biomechanics research.
This rapid movement can place unusual loads on the facet joints, joint capsules, muscles, ligaments, discs, and other tissues of the cervical region. The amount of loading varies considerably depending on factors such as collision dynamics, occupant position, head-restraint position, and individual characteristics.
In some injuries, cervical facet joints and their surrounding tissues may contribute to ongoing neck pain. However, the presence and extent of tissue injury cannot be determined from the collision mechanism alone. The biomechanics help us understand what may have been stressed, while the history and clinical examination help determine what is relevant to the individual patient.
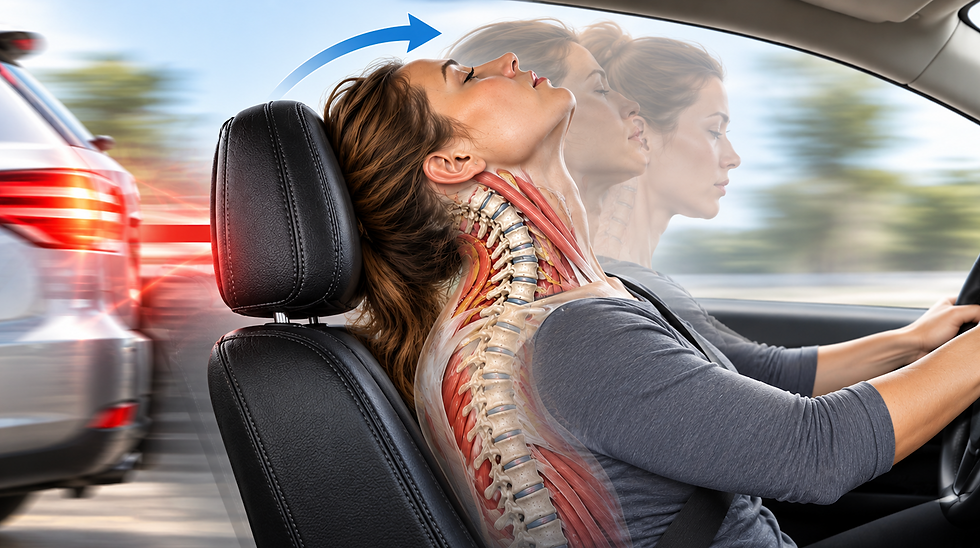
Stage 2: The Neck's Extension
As the vehicle and torso accelerate forward, the head begins to move backward relative to the body. This produces rapid extension of the cervical spine.
The amount of movement depends on several factors, including the direction and magnitude of the collision, the occupant's position, and the position of the head restraint. A properly positioned head restraint can help limit excessive rearward movement of the head.
During this phase, the joints and soft tissues of the cervical region can be exposed to rapid loading. However, the amount of tissue stress or injury varies considerably between individuals and cannot be determined from the collision mechanism alone.

Structures That May Be Affected
The initial impact and extension phase can load several structures within and around the cervical spine. These structures do not necessarily become injured in every whiplash event, but understanding their anatomy helps explain the range of symptoms that can occur.
Facet Joints and Joint Capsules
The cervical facet joints help guide and control movement between adjacent vertebrae. During rapid acceleration and extension, these joints and their surrounding capsules can experience substantial mechanical loading.
Research suggests that cervical facet joints can be a source of persistent neck pain in some people following whiplash. This does not mean that facet injury can be assumed simply because a rear-end collision occurred.
Cervical Ligaments
Ligaments contribute to the stability of the cervical spine and help limit excessive movement. Rapid acceleration-deceleration forces can place these tissues under considerable strain.
The anterior longitudinal ligament (ALL) runs along the front of the vertebral bodies and contributes to limiting excessive extension. Significant ligament injury is possible with trauma, but the presence and severity of ligament damage require appropriate clinical assessment and, when indicated, imaging.
Longus Colli
The longus colli is one of the deep muscles located along the front of the cervical spine. Together with other deep cervical muscles, it contributes to neck movement, segmental control, and cervical stability.
Changes in deep cervical muscle function and motor control have been identified in some people with persistent neck pain and whiplash-associated disorders. Rather than assuming that the longus colli has been physically “damaged,” examination should consider how the cervical musculature is functioning following the injury.
Platysma
The platysma is a thin, superficial muscle extending from the upper chest and shoulder region toward the lower jaw and face. It is innervated by the facial nerve.
Although superficial tissues such as the platysma may be exposed to rapid stretching during trauma, facial or upper-chest tingling should not automatically be attributed to injury of this muscle. Sensory symptoms require consideration of neurological and other potential causes.
Scalene Muscles and the Brachial Plexus
The scalene muscles lie along the sides of the neck and contribute to cervical movement and breathing. The brachial plexus passes between the anterior and middle scalene muscles, while important vascular structures also travel through this region.
Pain, muscle guarding, or altered movement involving this region may occur following trauma. Symptoms extending into the arm or hand, however, can have many possible causes, including cervical nerve-root irritation, peripheral nerve involvement, or other neurological and musculoskeletal conditions.
Thoracic outlet syndrome should not be assumed simply because the scalene muscles are painful or tight.
Sternocleidomastoid and Spinal Accessory Nerve
The sternocleidomastoid (SCM) is a large superficial neck muscle involved in cervical rotation, flexion, and control of head position. Like other cervical muscles, it may become painful, sensitive, or function differently following a whiplash injury.
The spinal accessory nerve supplies the SCM and trapezius muscles. Injury to this nerve is uncommon but can produce characteristic weakness and altered shoulder or neck function and warrants appropriate neurological assessment.
Headache and pain at the base of the skull can also accompany whiplash, but these symptoms have several possible sources. Occipital neuralgia should not be attributed to SCM compression without appropriate clinical evidence.

Stage 3 - Hyper-Flexion
Following the extension phase, the head and torso begin moving forward. Depending on the collision and restraint system, the cervical spine may move rapidly into flexion before the body finally decelerates.
Seatbelts play an important role in controlling movement of the torso and reducing the risk of more serious injury. Even with appropriate restraints, however, the rapid change in direction can expose the cervical spine and surrounding tissues to substantial mechanical loading.
As with the earlier phases of whiplash, the amount of movement and tissue loading varies considerably between collisions and individuals. The mechanism tells us which structures may have been stressed, but it does not establish which tissues were actually injured.
Structures That May Be Affected During Flexion
During rapid cervical flexion, muscles, ligaments, joints, discs, and other tissues of the neck help control and decelerate movement. This can contribute to pain, stiffness, muscle guarding, and changes in movement following a collision.
Facet Joints and Other Cervical Structures
The cervical facet joints and their surrounding capsules are exposed to changing loads throughout the whiplash sequence. Research suggests that the facet joints can be an important source of persistent neck pain in some people following whiplash.
However, neck pain following a collision can arise from multiple structures, and facet involvement cannot be determined from the mechanism of injury alone.
Posterior Cervical Muscles
The muscles along the back of the cervical spine help control head and neck movement and contribute to cervical stability and endurance.
Research using MRI has identified changes in the composition of some cervical muscles in certain people with persistent whiplash-associated disorders, including increased fatty infiltration. These findings are particularly interesting because they suggest that persistent WAD can be associated with measurable changes in the cervical muscular system.
However, these changes should not simply be interpreted as evidence that the muscles were physically torn or permanently damaged during the original collision. Persistent pain, altered muscle use, reduced activity, neurological factors, and other processes may contribute.
The Suboccipital Muscles
The suboccipital muscles are a group of small muscles located at the base of the skull. They contain a high concentration of sensory receptors involved in detecting head and neck position and contribute to fine control of cervical movement.
This makes the upper cervical region particularly interesting in whiplash rehabilitation. Changes in cervical proprioception and sensorimotor control have been identified in some people with persistent WAD and may contribute to symptoms such as impaired head-position accuracy, balance disturbances, or difficulty coordinating head and eye movements.
These symptoms should not automatically be attributed to damage of a particular suboccipital muscle or nerve. Dizziness and balance disturbances following a collision can have cervical, vestibular, neurological, visual, cardiovascular, medication-related, or concussion-associated contributors and require appropriate assessment.
Semispinalis, Splenius and Multifidus
The semispinalis, splenius, and multifidus muscles form part of the deeper and more superficial muscular system controlling cervical extension, rotation, stability, and movement.
Following whiplash, these muscles may become painful, sensitive, or demonstrate altered recruitment, endurance, or coordination. In persistent WAD, research has also identified structural and functional changes in some of the deeper cervical muscles.
Rather than attempting to identify one injured muscle as the source of persistent symptoms, examination should consider how the cervical muscular system is functioning as a whole.
Moving to Part 2
Understanding the biomechanics of whiplash helps explain how the cervical spine and surrounding tissues may be exposed to rapid and unusual loading during a collision. However, the mechanism of injury alone cannot tell us which structures are responsible for an individual's symptoms or how those symptoms will develop.
Part 2 examines the symptoms associated with whiplash, how these injuries are assessed, and how Whiplash-Associated Disorders are diagnosed and classified.
References
Bogduk, N. (2011). On cervical zygapophysial joint pain after whiplash. Spine, 36(25 Suppl), S194–S199.
Elliott, J. M., O'Leary, S., Sterling, M., Hendrikz, J., Pedler, A., & Jull, G. (2010). Magnetic resonance imaging findings of fatty infiltrate in the cervical flexors in chronic whiplash. Spine, 35(9), 948–954.
Elliott, J. M., Sterling, M., Noteboom, J. T., Treleaven, J., Galloway, G., & Jull, G. (2009). The clinical presentation of chronic whiplash and the relationship to findings of MRI fatty infiltrates in the cervical extensor musculature: A preliminary investigation. European Spine Journal, 18(9), 1371–1378.
Panjabi, M. M., Pearson, A. M., Ito, S., Ivancic, P. C., & Wang, J. L. (2004). Cervical spine curvature during simulated whiplash. Clinical Biomechanics, 19(1), 1–9.
Siegmund, G. P., Winkelstein, B. A., Ivancic, P. C., Svensson, M. Y., & Vasavada, A. (2009). The anatomy and biomechanics of acute and chronic whiplash injury. Traffic Injury Prevention, 10(2), 101–112.
Treleaven, J., Jull, G., & LowChoy, N. (2006). The relationship of cervical joint position error to balance and eye movement disturbances in persistent whiplash. Manual Therapy, 11(2), 99–106.
Disclaimer:
The articles and embedded videos on the MSR website are provided for educational and informational purposes only. They are not a substitute for individualized assessment, diagnosis, or treatment by an appropriately qualified healthcare professional.
Some videos demonstrate clinical examination and manual therapy procedures intended for licensed or regulated healthcare professionals with appropriate training. These procedures should be performed only within the practitioner’s legal scope of practice and should not be attempted as self-treatment.
Viewing or using this content does not establish a practitioner-patient relationship. If you have questions about a medical condition or symptoms that are new, severe, or worsening, consult an appropriately qualified healthcare provider.
MSR is not responsible for decisions made or actions taken solely on the basis of this educational content. For complete information about website use, third-party links, privacy, and legal terms, please review the MSR Terms of Use, Privacy Policy, and full website disclaimer.
DR. BRIAN ABELSON, DC. - The Author

Dr. Brian Abelson is a chiropractor, author, and educator with more than 30 years of clinical experience in musculoskeletal care, rehabilitation, and sports performance. His educational work focuses on musculoskeletal conditions, human movement, sports biomechanics, and evidence-informed approaches to treatment and rehabilitation.
He is the developer of Motion Specific Release (MSR) and Clinical Director of Kinetic Health in Calgary, Alberta, Canada.

Continue Learning with MSR Courses and MSR Pro
For Healthcare Practitioners
Motion Specific Release integrates assessment, clinical reasoning, manual therapy, exercise, and patient education within one adaptable approach to musculoskeletal care.
MSR Pro and MSR courses support different parts of that learning process:
Structured Clinical Education: MSR courses connect applied anatomy and biomechanics with orthopedic and neurological assessment, myofascial procedures, fascial expansions, joint mobilization, manipulation, and rehabilitation.
Hands-On Skill Development: Live training provides opportunities to refine palpation, patient positioning, force application, and clinical decision-making through practice and direct feedback.
MSR Pro Clinical Library: Members receive access to more than 200 MSR procedures, downloadable and fillable clinical forms, examination resources, rehabilitation progressions, and exercise-prescription materials.
Extensive Video Resources: More than 800 videos support examination, treatment procedures, exercise rehabilitation, and clinical application.
Patient Education: A library of 50 condition articles helps practitioners explain common musculoskeletal problems and provide patients with practical information.
Continued Development: Resources are updated as MSR courses and clinical education continue to evolve.
Videos and articles can introduce concepts, but hands-on proficiency develops through deliberate practice, feedback, and experience. MSR is designed to help practitioners connect technique with clinical reasoning and adapt care to the individual rather than apply the same protocol to everyone.
Explore MSR Pro | View Online and Live Courses



Comments